

Yesterday, I exposed how the New York Times tries to deceive its readers into believing that the decline in infectious disease mortality that occurred in the twentieth century was caused by vaccines.
Citing a review of vital statistics in the journal Pediatrics, Secretary of Health and Human Services Robert F. Kennedy, Jr. informed a Senate committee on April 22 that the dramatic decline in measles and other disease mortality was mostly due to factors related to an increasing standard of living.
The author of the Times article, Sheryl Gay Stolberg, vainly tried to deny the truth of what Kennedy said and falsely accused him of mischaracterizing the study while herself doing precisely that. Talk about hypocrisy!
Kennedy is right. It is an incontrovertible point of fact from the historical data that vaccines couldn’t possibly have driven the decline in infectious disease mortality.
I provided an extensive quote from the Pediatrics paper showing in context how it does affirm that “90% of the decline in infectious disease mortality among US children occurred before 1940, when few antibiotics or vaccines were available.”
In addition to graphs for diphtheria and pertussis, I presented the following graph of the data on measles mortality that absolutely destroys the Times’ propaganda narrative:

Here, I’d like to delve a bit deeper into the historical data, with a particular focus on the polio vaccine.
Vaccines Didn’t Save Us
In 1977, the Milbank Memorial Fund Quarterly: Health and Society published a paper by John B. McKinlay and Sonja M. McKinlay titled “The Questionable Contribution of Medical Measures to the Decline of Mortality in the United States in the Twentieth Century”.
In it, they focused on vaccinations and argued that, contrary to official dogma, most of the decline in infectious disease mortality had nothing to do with vaccines—an argument considered heretical at the time.
As they wrote:
The modern “heresy” that medical care (as it is traditionally conceived) is generally unrelated to improvements in the health of populations (as distinct from individuals) is still dismissed as unthinkable in much the same way as the so-called heresies of former times.
Of course, this “heresy” is recognized today as uncontroversially true, as shown by the Pediatrics review’s admission about what the data show.
In addition to a mythologized and dogmatic perception of the role of vaccines, the McKinlays pointed out the existence of institutionalized confirmation bias within the medical establishment:
One difficulty is that, depending on the nature of the results, double standards of rigor seem to operate in the evaluation of different studies. Not surprisingly, those which challenge prevailing myths or beliefs are subject to the most stringent methodological and statistical scrutiny, while supportive studies, which frequently employ the flimsiest impressionistic data and inappropriate techniques of analysis, receive general and uncritical acceptance.
I have made the same observation regarding studies examining health outcomes between vaccinated and unvaccinated children—with the data showing that unvaccinated children are healthier.
For more on how this reality is concealed from public view, see my book The War on Informed Consent: The Persecution of Dr. Paul Thomas by the Oregon Medical Board.
The problem is that good studies finding unvaccinated children to be healthier are offhandedly dismissed while studies systematically biased in favor of finding no harms from vaccines are touted as conclusive.
The clear criterion by which we are supposed to regard a study as valid or “fatally flawed” is whether it supports public vaccine policy or calls it into question.
For more on how this reality is concealed from public view, see my book The War on Informed Consent: The Persecution of Dr. Paul Thomas by the Oregon Medical Board.
The McKinlays also observed the “absurdity” of the belief that medical interventions were responsible for the dramatic decline in mortality:
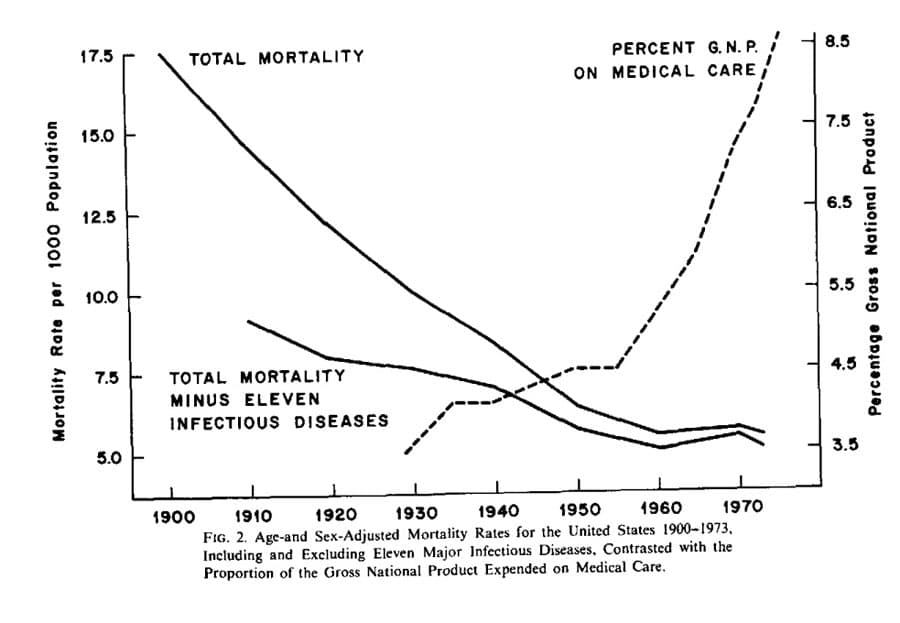
It is evident that the beginning of the precipitate and still unrestrained rise in medical care expenditures began when nearly all (92 percent) of the modern decline in mortality this century had already occurred.
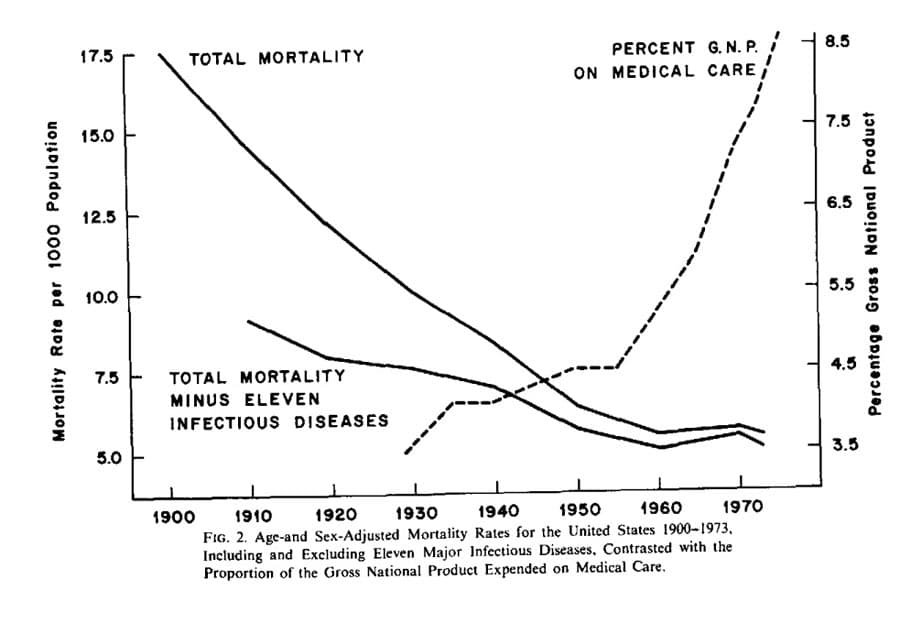
While health care spending has skyrocketed, so have rates of chronic illnesses. The ruling establishment wants you to think that’s a coincidence. Don’t believe them.
Commenting on specific diseases, the McKinlays observed (emphasis added):
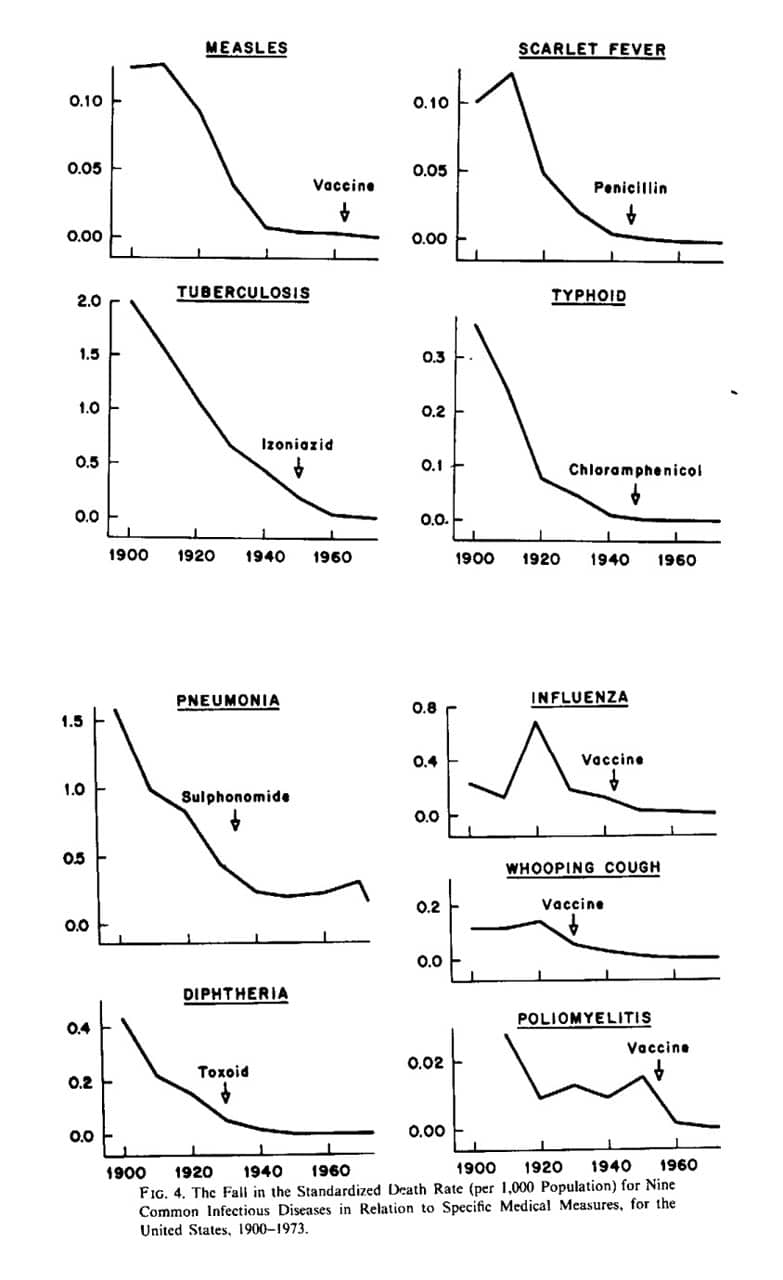
Disregarding smallpox (for which the only effective measure had been introduced about 1800), only influenza, whooping cough, and poliomyelitis show what could be considered substantial declines of 25 percent or more after the date of medical intervention. However, even under the somewhat unrealistic assumption of a constant (linear) rate of decline in the mortality rates, only whooping cough and poliomyelitis even approach the percentage which would have been expected. The remaining six conditions (tuberculosis, scarlet fever, pneumonia, diphtheria, measles, and typhoid) showed negligible declines in their mortality rates subsequent to the date of medical intervention.
In order to examine more closely the relation of mortality trends for these diseases to the medical interventions, graphs are presented for each disease in Fig. 4. Clearly, for tuberculosis, typhoid, measles, and scarlet fever, the medical measures considered were introduced at the point when the death rate for each of these diseases was already negligible. Any change in the rates of decline which may have occurred subsequent to the interventions could only be minute. Of the remaining five diseases (excluding smallpox with its negligible contribution), it is only for poliomyelitis that the medical measure appears to have produced any noticeable change in the trends. Given peaks in the death rate for 1930, 1950 (and possibly for 1910), a comparable peak could have been expected in 1970. Instead, the death rate dropped to the point of disappearance after 1950 and has remained negligible. The four other diseases (pneumonia, influenza, whooping cough, and diphtheria) exhibit relatively smooth mortality trends which are unaffected by the medical measures, even though these were introduced relatively early, when the death rates were still notable.
The authors concluded (bold emphasis added):
In general, medical measures (both chemotherapeutic and prophylactic) appear to have contributed little to the overall decline in mortality in the United States since about 1900—having in many instances been introduced several decades after a marked decline had already set in and having no detectable influence in most instances. More specifically, with reference to those five conditions (influenza, pneumonia, diphtheria, whooping cough, and poliomyelitis) for which the decline in mortality appears substantial after the point of intervention—and on the unlikely assumption that all of this decline is attributable to the intervention—it is estimated that at most 3.5 percent of the total decline in mortality since 1900 could be ascribed to medical measures introduced for the diseases considered here.
But What About Polio?
As the McKinlays indicated, the polio vaccine represents the best argument that can be made in favor of vaccination contributing to the dramatic decline in infectious disease mortality observed during the 20th century.
So, let’s take a closer look at the polio vaccine.
As with measles and other vaccines, we’re supposed to believe that the polio vaccine was responsible for the decline in disease incidence following its introduction.
However, as always, there is much more to the story that mainstream accounts leave out.
One fact always omitted from the official legend is how the decline in paralytic polio was largely a statistical artifact from changes in diagnostic criteria.
In essence, paralysis from other causes had previously been falsely attributed to the poliovirus, and at the same time the vaccine was introduced, diagnostic criteria were updated to more precisely define the probable cause of paralysis.
This was explained to the US House of Representatives Committee on Interstate and Foreign Commerce in May 1962 by Dr. Bernard Greenberg, the head of the department of biostatistics at the University of North Carolina’s School of Public Health and a former chairman of the evaluation and standards committee of the American Public Health association.
Dr. Greenberg testified that the “major disappointment” of Jonas Salk’s inactivated poliovirus vaccine was that it did not stop infection, and people who got the vaccine still had to experience infection to be “capable of achieving a more consistent immunity against the disease.”
Despite the vaccine’s availability, in 1958 and 1959, cases were on the rise again, which the Public Health Service (PHS) blamed on people choosing not to be vaccinated.
Dr. Greenberg described that claim as “[o]ne of the most obvious pieces of misinformation being delivered to the American public”.
He observed that the numbers of unvaccinated people were greater during the period when the vaccine was being credited with the decline than the period when cases increased again. Then he inquired (emphasis added):
Could it be that the vaccine has been only a temporary stopgap and that the effect is now wearing off because the vaccinated individuals are not maintaining their antibody status through subclinical exposures and booster doses?
One cannot answer this question in the negative with real assurance because such a possibility is certainly a real one. The reduction of antibody titer with time is well documented and may explain why some individuals vaccinated 5 years ago have lost their immunization status. . . .
A scientific examination of the data, and the manner in which the data were manipulated, will reveal that the true effectiveness of the present Salk vaccine is unknown and greatly overrated.
Greenberg explained how the vaccine that underwent field trials in 1954 was not the same as that administered since 1955.
The original vaccine had contained “merthiolate”, otherwise known as the mercury-based preservative thimerosal, which was removed.
In some lots of the original vaccine, live poliovirus was found, resulting in cases of vaccine-caused paralytic polio—such as the infamous “Cutter incident”.
To increase safety, “an extra filtration step was introduced in November 1955”, and the result of the change on the vaccine’s effectiveness was “unknown.”
Greenberg and colleagues conducted a study finding that “one dose was practically ineffective and two doses would produce a figure of only about 60 percent reduction among children 5 to 9 years old.”
He further commented on how the perceived decline in reported cases from 1955 through 1957 was largely “a statistical artifact”—attributable to incentives for physicians to report cases of paralytic poliomyelitis and changes in diagnostic criteria.
His explanation is worth quoting at length (emphasis added):
Prior to 1954 any physician who reported paralytic poliomyelitis was doing his patient a service by way of subsidizing the cost of hospitalization and was being community-minded in reporting a communicable disease. The criterion of diagnosis at that time in most health departments followed the World Health Organization definition: “Spinal paralytic poliomyelitis: sign and symptoms of nonparalytic poliomyelitis with the addition of partial or complete paralysis of one or more muscle groups, detected on two examinations at least 24 hours apart.”
Note that “two examinations at least 24 hour apart” was all that was required. Laboratory confirmation and presence of residual paralysis was not required. In 1955 the criteria were changed to conform more closely to the definition used in the 1954 field trials: residual paralysis was determined 10 to 20 days after onset of illness and again 50 to 70 days after onset. The influence of the field trials is still evidence in most health departments; unless there is residual involvement at least 60 days after onset, a case of poliomyelitis is not considered paralytic.
This change in definition meant that in 1955 we started reporting a new disease, namely, paralytic poliomyelitis with a longer lasting paralysis. Furthermore, diagnostic procedures have continued to be refined. Coxsackie virus infections and aseptic meningitis have been distinguished from paralytic poliomyelitis. Prior to 1954 large numbers of these cases undoubtedly were mislabeled as paralytic poliomyelitis. Thus, simply by changes in diagnostic criteria, the number of paralytic cases was predetermined to decrease in 1955–1957, whether or not any vaccine was used. At the same time, the number of nonparalytic cases was bound to increase because any case of poliomyelitis-like disease which could not be classified as paralytic poliomyelitis according to the new criteria was classified as nonparalytic poliomyelitis. Many of these cases, although reported as such, were not nonparalytic poliomyelitis. If this inaccurate number of cases of nonparalytic poliomyelitis reported in 1957 is accepted as accurate and considered as a base for subsequent comparisons, it is no wonder that we now say nonparalytic cases went down in 1958.
There is still another reason for the decrease in the reported paralytic poliomyelitis cases in 1955–57. As a result of the publicity given the Salk vaccine, the public questioned the possibility of a vaccinated child developing paralytic poliomyelitis. Whenever such an event occurred, every effort was made to ascertain whether or not the disease was truly paralytic poliomyelitis. In fact, I am certain that many health officers and physicians here will ask routinely if a child has been vaccinated when signs of poliomyelitis are present during the summer months. We have been conditioned today to screen out false positive cases in a way that was not even imagined prior to 1954.
As a result of these changes in both diagnosis and diagnostic methods, the rates of paralytic poliomyelitis plummeted from the early 1950’s to a low in 1957.
To summarize, the perceived decline in cases was largely attributable to changing diagnostic criteria and an institutionalized confirmation bias whereby the poliovirus tended to be the assumed cause of paralysis in unvaccinated patients, whereas further steps would be taken to determine the cause if the patients were vaccinated.
At the same hearing, Dr. Herman Kleinman, an epidemiologist from the Minnesota Department of Public Health, supported Greenberg’s suggestion that cases were rising because of waning of vaccine-induced protection (emphasis added):
Let me tell you why, aside from the statistical standpoint, I’m getting nervous about the Salk vaccine. My first reason is the definite increase in paralytic polio. In Minnesota we have found that 20 percent of our 1959 paralytic experience has occurred in triple and quadruple vaccinates. . . .
Laboratory findings are another reason why I am getting nervous. If polio antibodies mean anything in respect to protection, then I am forced to conclude that much of the Salk vaccine we have been using is useless. For 2 years now we have done antibody titrations on children who have received three or more doses of Salk vaccine. These titrations show that over 50 percent do not have antibodies to types I and III and that 20 percent lack antibodies to type II polio virus. This is a very disturbing fact. When a phenomenon like this occurs 2 years in a row, one has reason to believe that the material we are injecting is not an antigenic preparation.
Dr. Herald R. Cox, who was developing an orally administered polio vaccine, further elucidated the problem:
We are now learning, not only in the United States but in Israel, England, and Denmark, that the killed product does a fairly good job of producing antibodies against type II poliovirus. But type II represents only about 3 percent of paralytic cases throughout the world. The killed vaccine does a poor job against type I, however, which causes 85 percent of paralytic cases, and against type III, which causes about 12 percent. In other words, the killed vaccine is doing its best job against the least important type. It took time to find this out. It was proven in Israel in 1958, when it had its big type I epidemic. They did not see any difference in protection between the vaccinated and the unvaccinated. Last year in Massachusetts during a type III outbreak, there were more paralytic cases in the triple vaccinates than in the unvaccinated.
Asked whether harm was being done by use of the Salk vaccine, Dr. Cox affirmed that possibility (emphasis added):
[W]ith a low antigen killed vaccine you stand the danger of actually doing more harm than good.
The first field evidence we’ve had that there may be something to this clinically was the type III polio epidemic in Massachusetts last year, where 47 percent of the paralytic cases occurred in those who had three or more injections of the Salk vaccine. The lower incidence of paralytic polio (37 percent) in the unvaccinated group raises the question as to whether we have produced a greater sensitivity in the vaccinated individual.
Commenting on the inability of the vaccine to prevent infection, Dr. Cox stated, “The gastrointestinal tract must be made so resistant that wild strains cannot get a foothold. This cannot be done with a killed vaccine.”
The “live” oral polio vaccine was under development by Dr. Albert Sabin, which was anticipated to prevent infection—but which also risked causing paralytic polio in vaccinated individuals.
In fact, that is precisely why the oral polio vaccine was eventually phased out again in the US. Every case of paralytic polio in the US after 1979 was caused by the oral polio vaccine.
Nevertheless, in the Federal Register in 1984, the US Food and Drug Administration (FDA) declared with respect to the continued use of the orally administered vaccine, “any possible doubts, whether or not well founded, about the safety of the vaccine cannot be allowed to exist in view of the need to ensure that the vaccine will continue to be used to the maximum extent consistent with the nation’s public health objectives.” (Emphasis added.)
Today “vaccine-derived poliovirus”, or VDPV, is the key obstacle to global eradication of polio.
The artifactual decline in polio explained by Dr. Greenberg was reported by Joan Beck in the Chicago Tribune on March 5, 1961, in an article titled “The Truth About the Polio Vaccines”. As the Tribune observed (emphasis added):
Evaluating the true effectiveness of the Salk vaccine and the new oral vaccines has been difficult for several reasons. Polio is a relatively rare disease in the United States. Because so few persons get it in its paralyzing form, success of an immunizing agent is hard to determine.
The definition of polio also has changed in the last six or seven years. Several diseases which were often diagnosed as polio are now classified as aseptic meningitis or illnesses caused by one of the Coxsackie or Echo viruses. The number of polio cases in 1961 cannot accurately be compared to those in, say 1952, because the criteria for the diagnosis have changed.
Additionally, “Paralytic polio occurs in cycles and was in a natural decline when the Salk vaccine was introduced in 1955”, and a change in the definition of an “epidemic” had “resulted in a statistical—but not necessarily a real—drop in polio epidemics.”
Conclusion
To summarize, we are supposed to believe that vaccines caused the dramatic decline in infectious disease mortality witnessed during the 20th century, but the truth is that almost none of it could possibly have been caused by vaccinations.
The best case that can be made for a vaccine causing a substantial decline in disease mortality is the polio vaccine. But the data that are relied on to prove that the vaccine caused the decline are totally unreliable.
The apparent decline in cases of paralytic polio was largely a statistical artifact from changes in diagnostic criteria, and a resurgence of cases in the late 1950s is explainable by previously vaccinated individuals losing their protection—whereas natural infection was understood to confer lifelong immunity.
For more about how contemporary vaccination policies are grounded in historical myths that serve the pharmaceutical industry, read the book Dissolving Illusions by Dr. Suzanne Humphries and Roman Bystrianyk.
For more about how public vaccine policy violates fundamental human rights, read my book The War on Informed Consent.


